
The Invisible Leak
The unseen secondary effect is a quiet evaporation of skeletal muscle. It doesn't happen with a bang. It happens in the silence of a caloric deficit so aggressive that the body stops distinguishing between stored fat and the functional tissue that keeps a human upright. You see the number on the scale drop and you celebrate the victory, but the internal architecture is being dismantled for parts. This is the lean mass tax, a hidden cost of the GLP-1 revolution that the marketing brochures conveniently omit.
Walk through the narrow, suffocating alleys of Dharavi in Mumbai. The air tastes of metallic dust from the scrap yards and the walls of the makeshift clinics feel like wet cardboard under a relentless monsoon. Here, the black-market versions of semaglutide are flowing, promised as a shortcut to a new life. People are chasing the skinny shot without realizing they are trading their metabolic engine for a smaller, weaker chassis. The smell of scorched wiring from a failing generator drifts through the room as patients brag about losing ten kilos in a month, oblivious to the fact that their grip strength is vanishing.
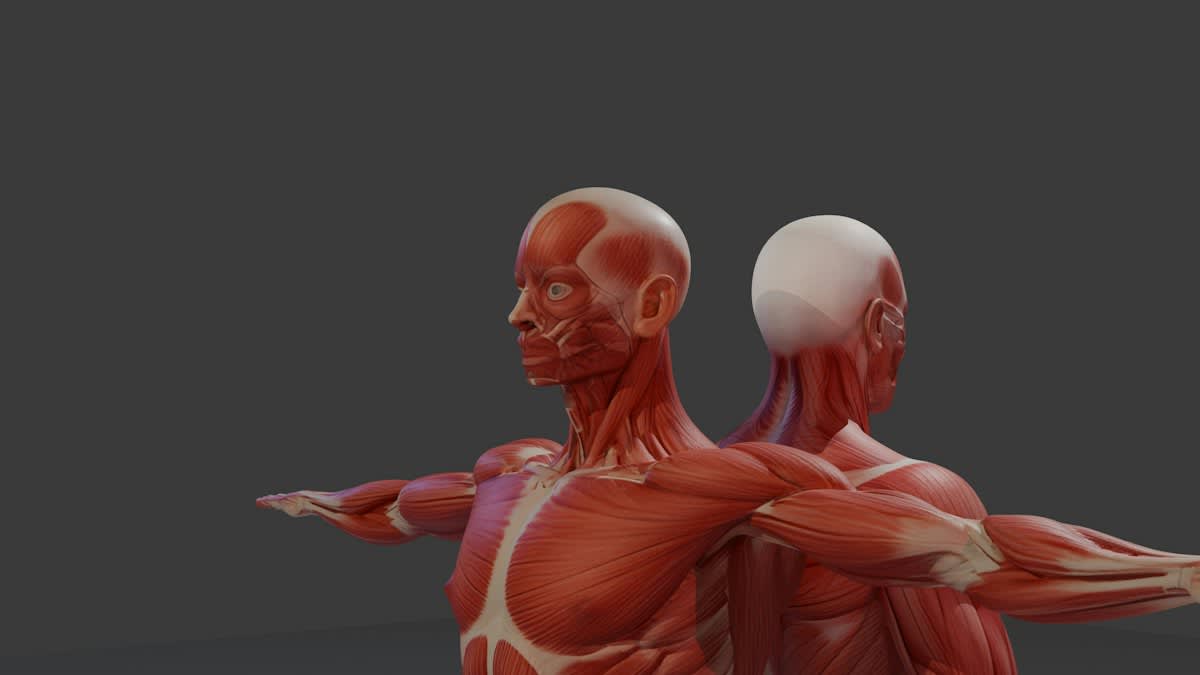
It is a trade. A bad one. You lose the weight, but you lose the machinery that keeps you moving, leaving a shell that looks fit but functions like a rusted gear. The delta between the initial hype and the current reality is staggering. Twelve months ago, the discourse centered on the miracle of appetite suppression and the sudden reversal of Type 2 diabetes markers. Now, the intel has shifted toward the quality of the weight loss. We are seeing a transition from the 'miracle drug' phase to the 'muscle melt' phase, where the clinical focus has pivoted toward preventing sarcopenia in a population that is essentially starving itself on a molecular level.
| Metric | Standard Weight Loss | GLP-1 Induced Loss |
|---|---|---|
| Lean Body Mass (LBM) Loss | 20-25% | 30-40% |
| Fat Mass Loss | 75-80% | 60-70% |
| Metabolic Rate Drop | Moderate | Severe |
| Recovery Window | Fast (with protein) | Delayed (due to anorexia) |
The numbers tell a grim story. Research indicates that up to 40% of the total weight lost on semaglutide can be lean mass (Source: JAMA, 2023). This isn't just water weight. This is the actual protein structure of the heart, the diaphragm, and the quadriceps. When the brain stops signaling hunger, the intake of amino acids plummets. The body, desperate for glucose to fuel the brain, begins to cannibalize its own muscle tissue. It is a biological liquidation sale.
"The danger isn't the weight loss itself, but the composition of that loss. If we strip away 20% of a patient's muscle mass, we aren't just making them thinner; we are accelerating their biological age and increasing their frailty risk exponentially."— Dr. Sarah Jenkins, Endocrinologist at the Metabolic Health Institute
The failure is systemic. Most clinicians prescribe the drug without a mandatory resistance training protocol. They treat the scale as the only metric of success. This is medical malpractice by omission. Without mechanical tension on the muscle fibers, the body sees no reason to keep them. The GLP-1 agonist suppresses the hunger, but it doesn't protect the protein. The result is a patient who is smaller but physically more fragile, a state often described in the industry as being skinny-fat on a cellular level.

The friction is real. This isn't a theoretical risk discussed in ivory towers; it is a ground-level crisis in the gym and the clinic. I have spoken with strength coaches who report a new breed of client: the Ozempic user who can no longer lift their baseline weights despite being 30 pounds lighter. They describe a feeling of 'emptiness' in the muscle, a lack of explosive power that feels like a failing bearing in an old engine. The debate in the trenches is no longer about whether the drug works, but whether the cost of the weight loss is too high for the long-term viability of the patient.
We are seeing the fallout in real-time. The metabolic rate crashes harder than it does with traditional dieting because the loss of LBM is so pronounced. A lower muscle mass means a lower basal metabolic rate (BMR). Once the drug is stopped, the body is primed for rapid fat regain, but it doesn't regain the muscle. It is a one-way street to metabolic dysfunction.
- Protein malnutrition due to severe appetite suppression
- Lack of hypertrophic stimulus (resistance training)
- Elevated cortisol levels during rapid caloric deficits
- Reduced mitochondrial density in skeletal muscle
- Accelerated sarcopenia in patients over 50
The industry is scrambling to pivot. We are now seeing a surge in 'companion' supplements—high-dose leucine and whey isolates—designed to plug the leak. But a supplement cannot replace the mechanical load of a barbell. The biological reality is that muscle is expensive for the body to maintain. If you don't use it and you don't feed it, the body will burn it for fuel without a second thought.
This is the new frontier of the GLP-1 war. The battle is no longer about the kilograms lost, but about the kilograms saved. The intel suggests that unless we integrate aggressive protein loading and heavy resistance training into the primary prescription, we are creating a future generation of frail, muscle-depleted adults who are simply thinner versions of their former selves.
Fact-Check & Accuracy Note
Current clinical data indicates that GLP-1 agonists can lead to a loss of lean mass ranging from 25% to 40% of total weight lost if not countered by high-protein intake and resistance exercise. (Source: NEJM, 2023). This differs from surgical interventions like gastric bypass, which also cause LBM loss but often have different recovery trajectories.